Why Most PCOS Treatment Misses the Root Cause
Polycystic ovary syndrome (PCOS) affects an estimated 8–13% of reproductive-age women worldwide — making it the most common endocrine disorder in this demographic — yet it remains significantly undertreated and mismanaged. The diagnostic criteria (Rotterdam 2003: two of three features — oligo/anovulation, clinical or biochemical hyperandrogenism, polycystic ovarian morphology on ultrasound) focus on symptoms without addressing causation. The treatment most commonly offered — oral contraceptives and, for fertility, clomiphene — manages symptoms without addressing the metabolic dysfunction driving them.
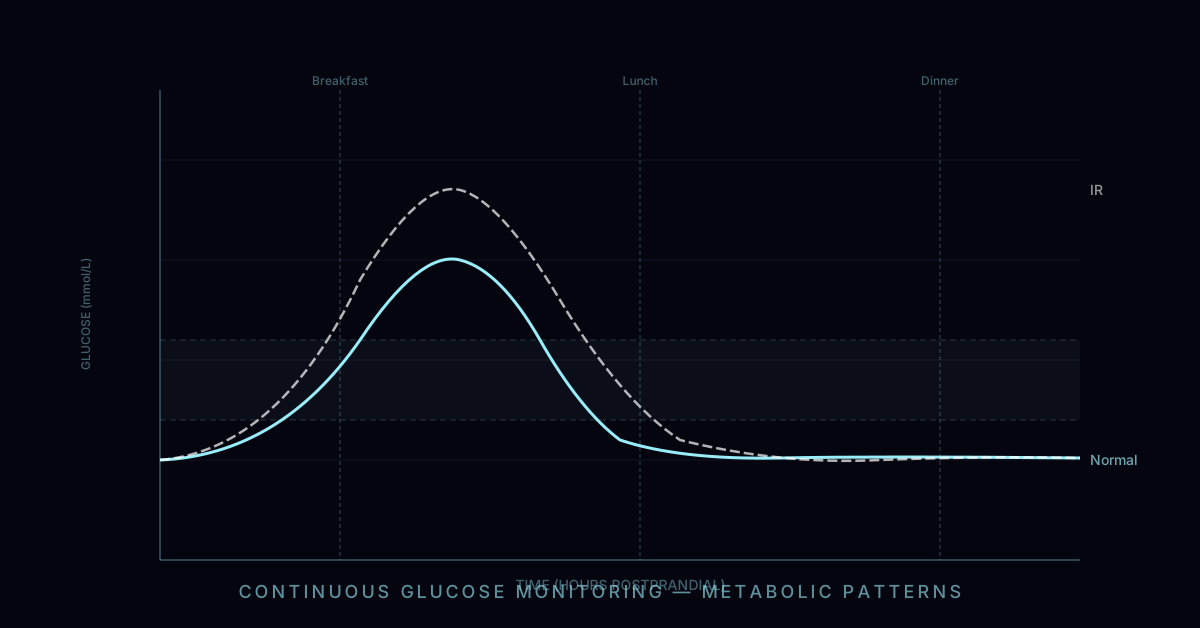
Approximately 65–80% of women with PCOS have insulin resistance as a central pathophysiological feature, and in these women, normalising insulin signalling is the most leverage-rich therapeutic target. When insulin resistance is corrected, androgens fall, SHBG rises, ovulation restores, and the symptoms that define PCOS — hirsutism, acne, irregular cycles, fertility challenges — improve independently of any symptom-directed treatment.
The Insulin-Androgen Pathway: Mechanism in Detail
The pathway from insulin resistance to PCOS symptoms is among the most well-established mechanisms in reproductive endocrinology. Hyperinsulinaemia — the elevated insulin that compensates for peripheral insulin resistance — acts directly on ovarian theca cells through insulin receptors that, paradoxically, remain insulin-sensitive even when muscle and liver cells are resistant. High insulin drives CYP17A1 (17α-hydroxylase/17,20-lyase) expression and activity in theca cells, amplifying androgen synthesis from cholesterol.
Simultaneously, hyperinsulinaemia suppresses hepatic SHBG production. SHBG (sex hormone-binding globulin) binds and inactivates circulating testosterone — when SHBG falls, free bioavailable testosterone rises even if total testosterone changes minimally. Women with PCOS have SHBG levels 40–60% below those of weight-matched controls, substantially amplifying the androgenic effect of even modest testosterone elevations.
High insulin also disrupts normal ovarian follicular development by promoting premature LH-like effects on small antral follicles, arresting their development at 2–9mm and preventing the single dominant follicle selection that normally leads to ovulation. The result is the characteristic ultrasound appearance — 12+ small peripheral follicles (the "string of pearls" or polycystic morphology) and the anovulation that drives irregular or absent menstrual cycles.
Essential Testing: What to Measure and Why
Standard PCOS management rarely includes insulin assessment — an extraordinary gap given that insulin resistance is the dominant pathophysiology in most patients. The minimum metabolic workup for PCOS should include:
- Fasting insulin — the most sensitive early marker. Optimal: 2–8 mIU/L. Above 10–12 mIU/L fasting suggests clinically significant insulin resistance even without glucose elevation.
- HOMA-IR — calculated from fasting glucose and insulin. Target <1.5. HOMA-IR >3.0 indicates significant insulin resistance.
- 2-hour OGTT with insulin — measures insulin dynamics beyond the fasting state; many PCOS patients have normal fasting insulin but exaggerated 1-hour insulin peaks (reactive hyperinsulinaemia) that are only captured with the OGTT.
- SHBG — a sensitive metabolic marker inversely correlated with insulin and androgens. Low SHBG (<30 nmol/L) indicates hyperinsulinaemic androgen excess and is an excellent treatment response marker.
- AMH — reflects ovarian follicle count; elevated in PCOS (>3.5 ng/mL). Normalises with effective treatment.
- Comprehensive metabolic panel, lipids, CBC — PCOS carries significantly elevated cardiovascular and T2DM risk.
Among the tests listed, SHBG and the 2-hour OGTT with insulin are the most underutilized in conventional PCOS management. SHBG is a cheap, reproducible marker that is more sensitive than fasting insulin alone for detecting hyperinsulinaemic androgen excess — a woman with SHBG of 20 nmol/L and "normal" fasting glucose almost certainly has significant insulin resistance that is missed by standard testing. The 2-hour OGTT with insulin measurements at 0, 30, 60, 90, and 120 minutes captures reactive hyperinsulinaemia — a pattern of high 1-hour insulin above 100 mIU/L despite normal fasting insulin — that is present in a substantial subset of PCOS patients and is entirely invisible to fasting-only assessments. Beyond diagnosis, baseline testing establishes the treatment response markers that allow objective monitoring: SHBG rising toward 40–50 nmol/L, fasting insulin falling below 8 mIU/L, AMH normalising, and HOMA-IR trending toward 1.5 are the measurable signals of effective intervention and should be re-checked at 3-month intervals.
Inositol: The Evidence-Based First-Line Supplement
Myo-inositol (MI) and D-chiro-inositol (DCI) are second messengers in the insulin signalling cascade, and their combined supplementation is the best-evidenced nutraceutical intervention for insulin-driven PCOS. The physiological plasma ratio is 40:1 (MI:DCI), and the most efficacious supplementation protocol matches this ratio: 4000mg myo-inositol + 100mg D-chiro-inositol daily, divided into two doses with meals.
Multiple RCTs support this combination. A 2017 RCT (Monastra et al.) in 46 PCOS women found the 40:1 MI:DCI combination superior to MI alone for restoring ovulation, reducing androgens, and improving oocyte quality. A large Italian multicentre study (Unfer et al., 2017) found that the 40:1 ratio restored menstrual cyclicity in 76% of previously oligo-amenorrhoeic PCOS women over 6 months. The mechanism: MI supports FSH signalling in granulosa cells (essential for follicular maturation), while DCI reduces theca cell androgen synthesis through insulin sensitisation. The 40:1 ratio is critical — excess DCI paradoxically impairs MI-dependent FSH signalling in granulosa cells.
Berberine: The Evidence-Based Metformin Alternative
For patients who do not respond adequately to inositol alone, or who require more potent insulin sensitisation, berberine at 500mg three times daily with meals has demonstrated efficacy comparable to metformin in direct comparison RCTs, with additional lipid-lowering benefits. The 2012 Tan et al. JCEM head-to-head RCT (n=89) showed berberine and metformin equivalently reduced HOMA-IR, free testosterone, and LH:FSH ratio, with berberine producing superior lipid improvements. Berberine does not deplete vitamin B12 (a concern with long-term metformin use) and does not require a prescription.
The mechanism of berberine's insulin-sensitising action involves AMPK activation — the same pathway targeted by metformin. Berberine activates AMPK through inhibition of mitochondrial complex I (raising AMP:ATP ratio) and through additional upstream AMPK kinase stimulation, producing a multifactorial sensitising effect. In hepatic tissue specifically, berberine downregulates gluconeogenic gene expression (PEPCK, G6Pase) and upregulates hepatic insulin receptor expression — two effects that directly address the hepatic insulin resistance that contributes to fasting hyperinsulinaemia in PCOS. A 2015 Cochrane-style systematic review by Yin et al. across 27 RCTs (n=2,569) confirmed berberine's glycaemic efficacy was non-inferior to first-line oral antidiabetics including metformin and glipizide across multiple metabolic endpoints.
Practical prescribing considerations: berberine has significant drug interactions via CYP3A4 and P-glycoprotein inhibition — it increases plasma levels of metformin itself, cyclosporin, and some statins. Patients on prescription medications should review interactions with a physician before combining. GI side effects (loose stools, nausea, bloating) are common at initiation; starting at 500mg once daily and increasing over 2–3 weeks to the full 1,500mg/day dose substantially improves tolerability. The lipid improvements documented with berberine — LDL reduction of 20–25% in multiple trials — are an additional benefit given the elevated cardiovascular risk profile of insulin-resistant PCOS.
Exercise Timing and Type for PCOS
Exercise improves insulin sensitivity in PCOS through multiple mechanisms: increased GLUT4 translocation to muscle membranes (increasing glucose disposal without insulin), reduced visceral adiposity (which is disproportionately insulin-resistant), and reduction of chronic low-grade inflammation. The type and timing of exercise matters for PCOS specifically. Resistance training has been shown to be particularly effective for insulin sensitivity in PCOS — a 2011 RCT (Thomson et al.) found combined aerobic + resistance training superior to aerobic alone for reducing testosterone and improving ovulation. Morning exercise may be preferable for insulin-resistant PCOS: glycaemic control is worst in the morning (highest insulin resistance), and morning exercise has the most immediate impact on the day's glucose metabolism. HIIT (high-intensity interval training) appears particularly beneficial for improving insulin sensitivity in the specific context of PCOS, through mechanisms including post-exercise oxygen consumption and enhanced AMPK activation.
Volume and frequency recommendations for PCOS differ from general exercise guidelines. The 2023 PCOS Alliance consensus statement recommends a minimum of 150 minutes of moderate-intensity aerobic activity per week, but emphasises that resistance training (2–3 sessions per week targeting major muscle groups) is essential rather than optional. Skeletal muscle is the dominant site of insulin-mediated glucose disposal, accounting for 75–80% of post-meal glucose uptake; building and maintaining muscle mass through progressive resistance training has long-term insulin-sensitising effects that aerobic exercise alone cannot fully replicate. The combination of higher muscle mass (from resistance training) and improved cardiovascular capacity (from aerobic exercise) creates compounding benefits for insulin sensitivity and androgen metabolism.
One often-overlooked consideration for PCOS exercise: the HPA axis response to excessive training. Overtraining and chronic caloric deficit in the context of intensive exercise elevate cortisol — a glucocorticoid that directly promotes insulin resistance and increases visceral fat deposition. Women with PCOS already show a degree of HPA axis dysregulation, and extreme exercise programmes or very-low-calorie diets can worsen the cortisol-insulin dynamic. A 2020 systematic review found that exercise intensity above 70% VO2max performed without adequate caloric support was associated with elevated cortisol and paradoxically worsened insulin markers in PCOS. Moderate-intensity, progressive training with adequate fuelling is safer and more effective than high-intensity, calorie-restricted approaches for this condition.
The Complete PCOS Protocol: Putting It Together
Evidence-based management of insulin-resistant PCOS integrates dietary, supplemental, pharmaceutical, and lifestyle interventions in a hierarchy from highest evidence to adjunctive support. First-line: low-glycaemic-index diet (target 35–40% calories from low-GI carbohydrates, 25–35g daily fibre, elimination of ultra-processed foods), combined with myo-inositol/D-chiro-inositol at the 40:1 ratio (4,000mg MI + 100mg DCI daily in two divided doses with meals). These two interventions address the insulin-androgen cycle at its root and have the most consistent RCT support for PCOS-specific outcomes.
Second-line, when first-line response is incomplete after 3 months: berberine 500mg three times daily with meals (or metformin 500–1,000mg twice daily under physician supervision for patients who prefer prescription therapy or have contraindications to berberine). Monitor HOMA-IR and SHBG at 3-month intervals — rising SHBG is the most sensitive early marker of treatment response; normalising SHBG above 40–50 nmol/L typically tracks with androgen normalisation and menstrual cycle restoration. Adjunctive supplementation with clinical evidence in PCOS: vitamin D (PCOS patients have high rates of vitamin D deficiency; supplementation to 25-OH-D levels above 50 ng/mL improves insulin sensitivity and ovulation independently); omega-3 fatty acids (2–3g EPA+DHA daily reduce triglycerides and chronic inflammation); magnesium (PCOS is associated with magnesium depletion; 300mg magnesium glycinate daily supports insulin signalling).
Exercise: 150+ minutes moderate aerobic plus 2–3 resistance training sessions weekly, with particular attention to avoiding excessive exercise stress that elevates cortisol. Timing of carbohydrate intake to post-workout windows (within 60 minutes of resistance training) improves partitioning toward muscle glycogen replenishment and away from adipose tissue storage. Sleep optimisation (7–9 hours, consistent timing) is an underemphasised pillar — even a single night of partial sleep deprivation (4–5 hours) measurably worsens insulin sensitivity the following day, and chronic sleep restriction substantially undermines any other PCOS intervention. The expected timeline with full protocol adherence is measurable HOMA-IR improvement within 6–8 weeks, androgen normalisation within 3–6 months, and menstrual cycle restoration within 6–12 months in the majority of insulin-resistant PCOS patients.